


Periodontology
Periodontitis
Inflammatory periodontal diseases associated with dental plaque are among the most common diseases in humans.

Periodontitis
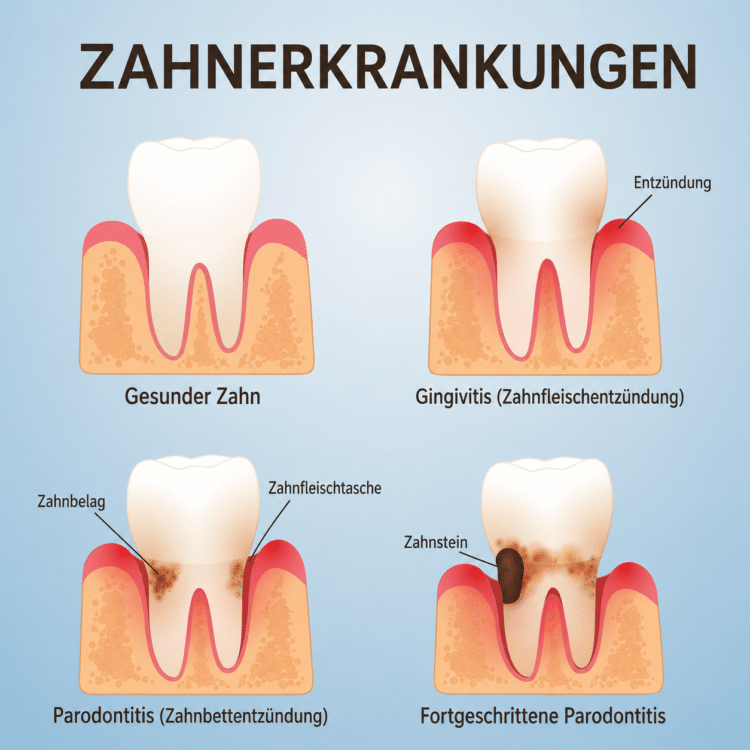
Periodontitis is a chronic disease of the tooth bed and the periodontium. It is usually caused by a bacterial infection, which first leads to gum inflammation (gingivitis) and can then, in the next stage, spread to the jawbone. If left untreated, periodontitis can even lead to tooth loss.
Periodontitis is very often only diagnosed in the fourth or even fifth decade of life, by which time the degree of destruction is usually already very advanced. The first signs of periodontitis can be recognised much earlier by a practitioner specialising in this field. The insidious thing about this chronic disease is that, because of its slow, painless and creeping course, those affected also notice it only very late. Don’t let it get that far – take advantage of preventive periodontal screening so that, should the need arise, we can intervene quickly and effectively.
Periodontitis — Continued
Gingivitis is regarded as a kind of precursor to periodontitis. It is triggered by a mixed bacterial infection, the so-called biofilm or “bacterial plaque”. If oral hygiene is neglected, such an acute inflammation can become established within a few days. Its clinical symptoms include, for example, redness and swelling of the gums or increased bleeding of the gums. The classic bite into an apple is familiar from advertising and can certainly be an indicator of gums that are not entirely healthy.
Once the dentist has diagnosed gingivitis, complete healing of the periodontal structures can be expected within a few weeks with appropriate therapeutic measures. A dental hygienist works with you to optimise your oral hygiene to the point where a healthy, strong periodontium very quickly forms again.
Chronic Periodontitis – Progression
If the body cannot defend itself against gingivitis and it is not recognised as a precursor to periodontitis, persistent inflammation can set further destructive processes in motion.
The bacterial toxins and the body’s own immune defence lead to the onset of breakdown of periodontal structures such as the periodontium and the jawbone. At this stage, treatment is already absolutely necessary!
If left untreated, the disease can progress ever deeper and ultimately lead to tooth loss. Of course, as with most diseases, the earlier it is detected, the better the chances of healing.
However, in this case it is a chronic disease that requires lifelong monitoring and therapy. The patient’s own motivation and cooperation, the so-called compliance, contributes significantly to the success of periodontitis therapy.

Systematic Periodontal Therapy
Systematic periodontal therapy is divided into several phases.
Ask your specialists at smileDentity
Andreas Haas I M.Sc. I Dentist (certified in periodontology)
&
Buschra Lemkadem I Dental Hygienist
Hygiene Phase I
The aim of the hygiene phases is to reduce or eliminate the germs that cause periodontitis. Poor dentures or leaking old fillings are a frequent cause of periodontitis, and the degree of destruction at these sites is particularly dramatic. In a kind of pre-treatment for the restorative phase, this poor dental prosthesis and the old or marginally leaking fillings must be replaced. Already in the hygiene phase, conditions must be created that enable the patient to carry out adequate oral hygiene independently.
Approx. 6–8 weeks after hygiene phase I, the condition of the gums is reassessed. In most cases, optimal hygienic conditions have already been achieved at this point, so that nothing stands in the way of the definitive, new, more aesthetic dental prosthesis. The restorative phase can be initiated.
Hygiene Phase II
If conditions are not quite so optimal, hygiene phase II should be carried out, either on the entire gums or locally at the critical sites. The treatment procedure is the same as in hygiene phase I.
Corrective Phase
The corrective phase describes a surgical procedure if hygiene phase II has still not led to the desired result. The overarching goal of this treatment phase is to create a morphology of hard and soft tissues that allows optimal cleaning by both the patient and the dental hygienist. Methodologically, regenerative treatment procedures are predominantly used here.
Pocket probing depths of 3 mm are regarded as the optimal result at the end of the hygiene phases or the corrective phase; among specialists this is also referred to as “zero pocket”.
Restorative Phase
Strictly speaking, the restorative phase is not part of periodontal treatment. Here, new aesthetic, functional and periodontally friendly restorations optimise the treatment result achieved and stabilise it in the long term. The interdisciplinary aspect becomes more than clear here.

Maintenance Phase
The maintenance phase serves to maintain the treatment result. Although it has a prophylactic character, it differs from primary prophylaxis in that the patients concerned have already been affected by the disease, even if they are currently symptom-free. Since the risk of recurrence is higher here than in a primarily healthy patient, individual recall intervals are set.
This supportive periodontal therapy (SPT) is carried out by a specially trained dental hygienist.
“Periodontitis therapy does not end after treatment – it remains stable through consistent maintenance. Every recall is an important step in detecting inflammation early and securing the result achieved in the long term.”
Buschra Lemkadem – Dental Hygienist
Periodontology – Treatment Techniques
In addition to classic conservative manual therapy, scaling/root planing (SRP for short) with hand instruments, which essentially still represents the gold standard, oscillating piezo instruments are also used. Piezo technology makes gentle, delicate and effective work deep in the pocket possible. To achieve a further reduction in germs in hygiene phase I or II, additional optional or adjuvant therapies are recommended.
Optional Therapies
Further bacterial reduction through the use of a diode laser. The laser can be used 2–3 days after the hygiene phases. Because the treatment is gentle, local anaesthesia is usually not necessary. The laser has a bacteria-sterilising, haemostatic and healing effect.
Most of the bacteria that cause periodontitis are eliminated by the laser treatment, making drug-based antibiotic therapy, with its side effects, unnecessary. Laser periodontitis treatment stops the loss of bone in the jawbone and stabilises the firmness of the teeth.
Adjuvant Therapies
A tiny chip measuring just 4×5 mm, containing the active ingredient chlorhexidine bound in a fine gelatine layer, dissolves completely after approx. 7–10 days – but remains effective for up to 3 months.
The tiny chip is inserted precisely into the previously treated gum pocket using tweezers. It disappears there completely and remains invisible from the outside. From this moment on, it begins to act against the bacteria that cause periodontitis.
Inflammatory periodontal diseases associated with dental plaque are among the most common diseases in humans. Let us advise you on the subject of periodontology.
Our spaces are best experienced in person.
Arrange a no-obligation introductory visit — we’ll show you the practice, discuss your wishes and answer your questions.